
Food poisoning
statistics UK
Explore the UK foodborne illness burden, ten-year infection trends, searchable regional comparisons and outbreak records, with original charts and downloadable evidence.

By Mark McShane
Updated 13 November 2026 · Latest published evidence

On this page
Key UK food poisoning statistics
estimated foodborne illnesses each year in the UK.
2018 model · Published 2020 [1]estimated annual hospital admissions from foodborne illness.
UK · Rounded 2018 model [1]estimated annual societal cost of foodborne disease.
UK · 2025 prices · FSA 2026 [7]- The national illness estimate has a wide uncertainty range: approximately 1.8–3.1 million cases a year. The model also estimates around 222,000 GP presentations. [1]
- Norovirus and Campylobacter account for the largest named-pathogen estimates in the 2018 model: about 383,000 and 299,000 foodborne illnesses respectively. A larger unattributed category covers illness without a named cause. [1]
- England recorded 69,489 Campylobacter and 10,401 non-typhoidal Salmonella laboratory reports in 2025, using the revised September 2026 release. These are not UK foodborne-only totals. [2]
- In January–June 2026, Campylobacter reports fell 4.4% and Salmonella reports rose 17.1% compared with the same six months of 2025. [2]
- England recorded 2,457 culture-confirmed STEC cases in 2025, plus 961 non-O157 reports detected by PCR without culture confirmation. [3]
- England and Wales recorded 181 listeriosis cases in 2025; 40 were pregnancy-associated and 141 were not. [3]
- Scotland’s new report records 6,357 Campylobacter and 875 non-typhoidal Salmonella reports in 2025. Both were lower than in 2024. [4]
- Twenty reported foodborne Campylobacter and Salmonella outbreaks affected 299 people in England in 2025. These investigated outbreaks represent only part of foodborne illness. [3]
- The FSA handled 2,073 food and feed safety incidents in 2025/26. That is an operational incident count across England, Wales and Northern Ireland, not 2,073 people with food poisoning. [9]
How many people get food poisoning in the UK?
The best verified UK-wide estimate is around 2.4 million foodborne illnesses per year. Routine testing cannot count every episode: many people recover without seeking medical care, and not every person who seeks care has a diagnostic sample. The FSA’s model combines research and surveillance to estimate the wider burden. [1]
The full model’s central estimate is 2,362,262 illnesses, with a 95% credible interval of 1,795,083–3,149,740. The familiar 2.4 million figure is a rounded estimate, not an exact census. The model has a separate unattributed-illness estimate of 1,449,168, reflecting the substantial share for which the cause is unknown. Medians from separate model distributions do not necessarily add exactly to the overall median.
| UK annual outcome | Central estimate | 95% credible interval |
|---|---|---|
| Foodborne illnesses | 2,362,262 | 1,795,083–3,149,740 |
| GP presentations | 222,207 | 149,964–322,347 |
| Hospital admissions | 16,439 | 11,410–26,119 |
These outcomes come from modelling rather than a single group followed through treatment. Dividing admissions or deaths from different models by the illness estimate would create a misleading severity rate. The uncertainty intervals express uncertainty in the estimates; they are not a range of observed annual totals.
The FSA’s 2026 research update describes the third Infectious Intestinal Disease study, IID3, and a further attribution exercise needed to translate intestinal illness into foodborne estimates. We have retained the established model while that replacement is pending. [1] [7]
Foodborne illness estimates by pathogen
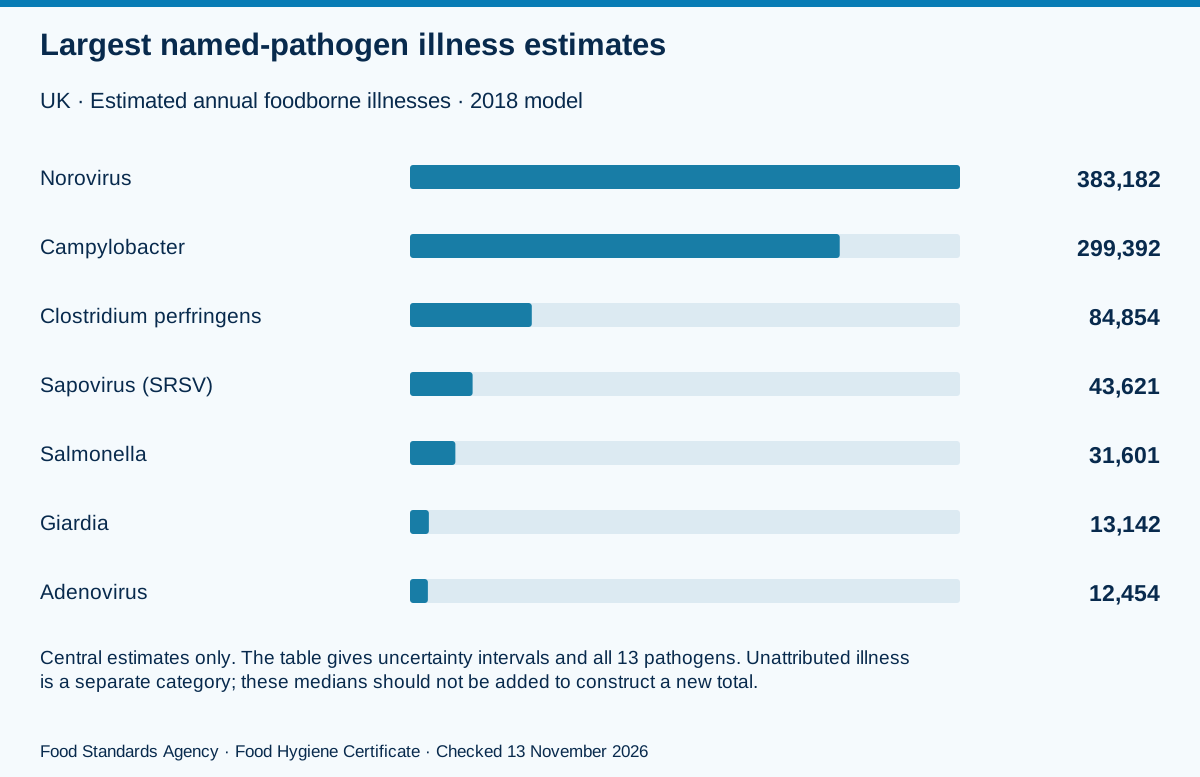
The 2018 model estimates foodborne illness from 13 named pathogens, alongside unattributed illness. Its largest named categories are norovirus, Campylobacter and Clostridium perfringens. These estimates describe illness attributed to food, which is a different measure from the latest laboratory reports below. [1]
UK · Estimated annual foodborne illnesses · 2018 model [1]
Central estimates only. The table gives uncertainty intervals and all 13 pathogens. Unattributed illness is a separate category; these medians should not be added to construct a new total.
| Pathogen | Estimated illnesses | 95% credible interval | GP presentations | Hospital admissions |
|---|---|---|---|---|
| Norovirus | 383,182 | Not published | 16,915 | 2,167 |
| Campylobacter | 299,392 | 127,128–571,332 | 42,506 | 3,505 |
| Clostridium perfringens | 84,854 | 32,044–224,637 | 13,458 | 376 |
| Sapovirus (SRSV) | 43,621 | 28,934–64,705 | 2,625 | 245 |
| Salmonella | 31,601 | 6,781–147,158 | 11,484 | 2,097 |
| Giardia | 13,142 | 2,034–71,127 | 1,512 | 28 |
| Adenovirus | 12,454 | 3,085–34,672 | 1,028 | 192 |
| Astrovirus | 2,552 | 573–7,993 | 192 | 36 |
| Cryptosporidium | 2,072 | 320–12,201 | 712 | 55 |
| Rotavirus | 2,065 | 518–5,670 | 220 | 32 |
| Shigella | 1,634 | 110–4,973 | 1,634 | 29 |
| E.coli O157 | 468 | 303–628 | 468 | 146 |
| Listeria monocytogenes | 162 | 146–170 | 162 | 139 |
Estimates are shown at the precision published so they can be checked against Table 3. This does not imply exact knowledge. The complete download includes uncertainty intervals for GP presentations and admissions too.
In this model, norovirus causes many illnesses while Campylobacter accounts for the largest named-pathogen hospital-admission estimate. A pathogen’s frequency and its tendency to cause severe illness are different questions.
Latest 2026 figures: compare the same months
England recorded 33,416 Campylobacter and 4,622 non-typhoidal Salmonella laboratory reports in January–June 2026. Campylobacter was down from 34,936 a year earlier; Salmonella was up from 3,947. These comparisons use the same release and the same six-month period. [2]
| Infection | Year | January–March | April–June | First-half total |
|---|---|---|---|---|
| Campylobacter | 2024 | 12,985 | 19,370 | 32,355 |
| Campylobacter | 2025 | 16,031 | 18,905 | 34,936 |
| Campylobacter | 2026 | 15,094 | 18,322 | 33,416 |
| Non-typhoidal Salmonella | 2024 | 1,541 | 2,386 | 3,927 |
| Non-typhoidal Salmonella | 2025 | 1,599 | 2,348 | 3,947 |
| Non-typhoidal Salmonella | 2026 | 2,021 | 2,601 | 4,622 |
Campylobacter decreased by 1,520 reports, or 4.4%, while Salmonella increased by 675, or 17.1%. Neither result is a full-year forecast. The figures include overseas-acquired infections and transmission other than food; changes in testing and reporting can also affect the totals.
How reported infections have changed
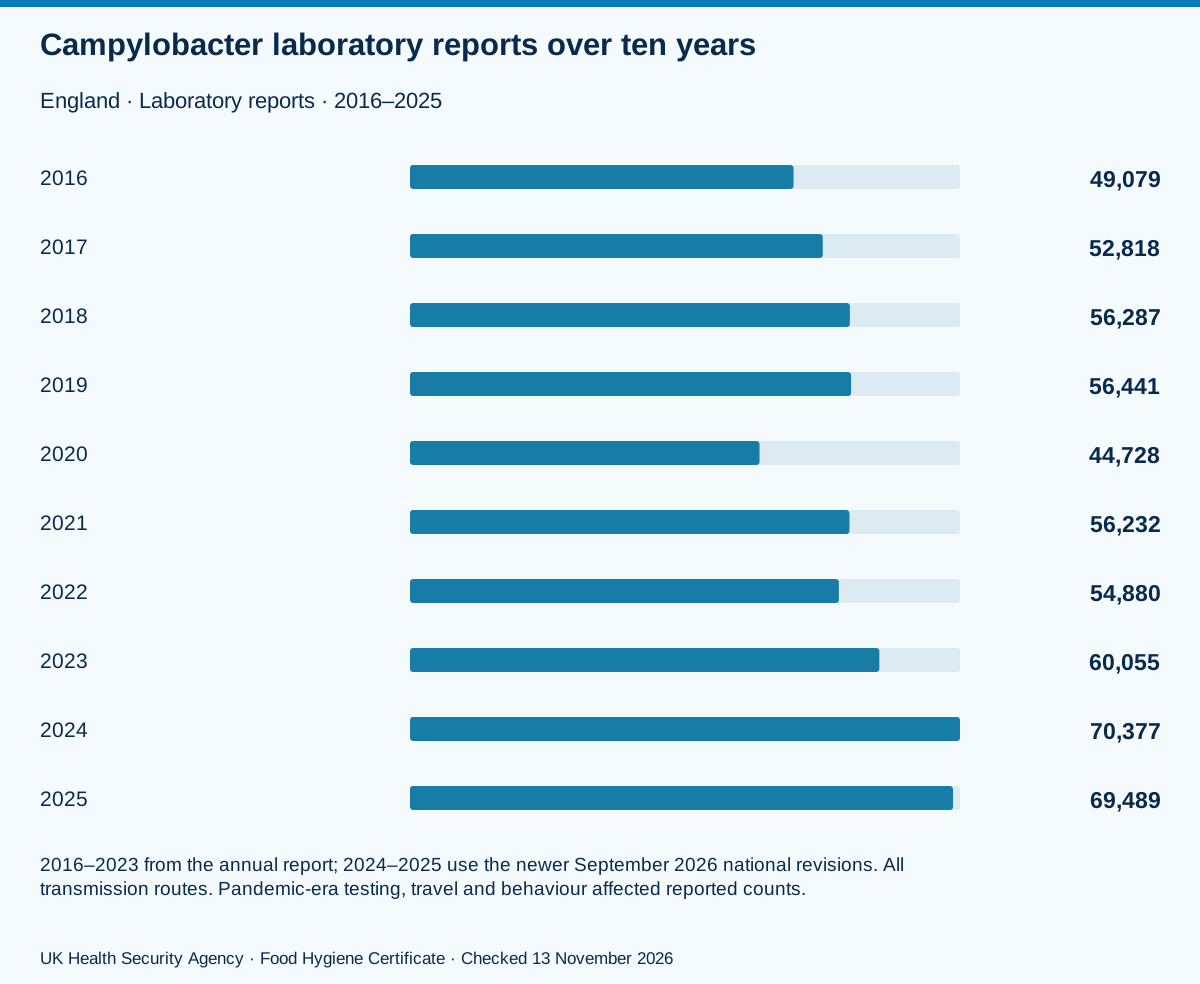
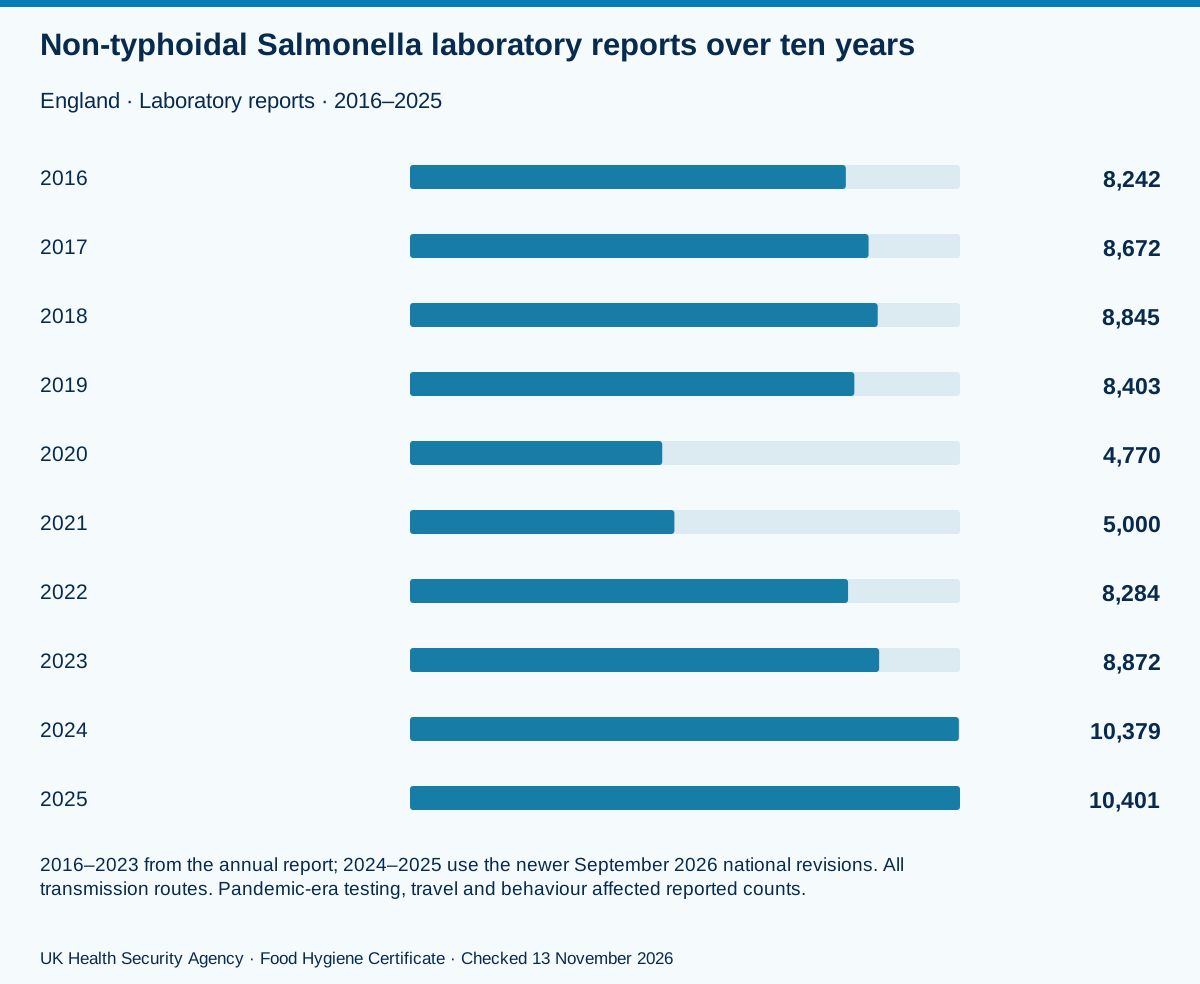
Using the latest revisions, England’s 2025 Campylobacter reports were 1.3% lower than the 70,377 recorded in 2024. Salmonella reports were 0.2% higher than 10,379. The longer series shows why a single-year change does not describe the whole picture. [2] [3]
England · Laboratory reports · 2016–2025 [2]
2016–2023 from the annual report; 2024–2025 use the newer September 2026 national revisions. All transmission routes. Pandemic-era testing, travel and behaviour affected reported counts.
England · Laboratory reports · 2016–2025 [2]
2016–2023 from the annual report; 2024–2025 use the newer September 2026 national revisions. All transmission routes. Pandemic-era testing, travel and behaviour affected reported counts.
| Year | Campylobacter reports | Salmonella reports |
|---|---|---|
| 2016 | 49,079 | 8,242 |
| 2017 | 52,818 | 8,672 |
| 2018 | 56,287 | 8,845 |
| 2019 | 56,441 | 8,403 |
| 2020 | 44,728 | 4,770 |
| 2021 | 56,232 | 5,000 |
| 2022 | 54,880 | 8,284 |
| 2023 | 60,055 | 8,872 |
| 2024 | 70,377 | 10,379 |
| 2025 | 69,489 | 10,401 |
Reported infections do not all move in the same direction. Changes can reflect real transmission, travel, outbreaks, diagnostic methods, late reporting and de-duplication. The charts do not establish how much each factor contributed, and the pandemic years need particular care when comparing trends.
Scotland: the latest 2025 results
Scotland’s report was published on 10 November 2026. Campylobacter reports fell from 6,729 to 6,357, a 5.5% reduction. Non-typhoidal Salmonella fell from 965 to 875, down 9.3%. These are laboratory reports for Scotland, separate from England’s surveillance. [4]
| Pathogen or reporting group | 2023 | 2024 | 2025 | Change from 2024 |
|---|---|---|---|---|
| Campylobacter | 5,930 | 6,729 | 6,357 | -5.5% |
| E. coli O157 | 133 | 167 | 138 | -17.4% |
| Non-O157 STEC | 182 | 293 | 210 | -28.3% |
| Listeria monocytogenes | 22 | 22 | 20 | -9.1% |
| Norovirus | 1,782 | 1,943 | 1,544 | -20.5% |
| Non-typhoidal Salmonella | 742 | 965 | 875 | -9.3% |
The Scottish E. coli O157 and non-O157 STEC series include PCR-positive reports without culture confirmation. They should not be compared directly with England’s culture-confirmed-only total. The downloadable evidence also contains the Scottish 2016–2025 series.
Campylobacter’s national count includes 13 reports for people who were not resident in Scotland. The health-board table below covers the remaining 6,344 resident reports. Small numbers in the Salmonella table are suppressed as “<5”; we retain that suppression.
Search the regional infection statistics
Compare published 2025 laboratory reports across nine English regions and fourteen Scottish NHS health boards. Filter by nation and infection, or search for an area. England includes Campylobacter, Salmonella and listeriosis; Scotland includes Campylobacter and Salmonella. [3] [4]
These are reporting rates by residence, not food-poisoning risk rankings. Testing, age profiles, reporting systems, travel and other transmission routes can affect comparisons. English regions and Scottish boards are different types of area, and small populations can produce volatile rates.
All published records are shown below.
| Area of residence | Nation | Infection | Reports | Rate per 100,000 |
|---|---|---|---|---|
| East Midlands | England | Campylobacter [3] | 5,303 | 104.7 |
| East Midlands | England | Listeriosis [3] | 9 | 0.18 |
| East Midlands | England | Non-typhoidal Salmonella [3] | 796 | 15.7 |
| East of England | England | Campylobacter [3] | 7,270 | 110.5 |
| East of England | England | Listeriosis [3] | 14 | 0.21 |
| East of England | England | Non-typhoidal Salmonella [3] | 1,133 | 17.2 |
| London | England | Campylobacter [3] | 9,075 | 99.8 |
| London | England | Listeriosis [3] | 38 | 0.42 |
| London | England | Non-typhoidal Salmonella [3] | 2,329 | 25.6 |
| North East | England | Campylobacter [3] | 3,961 | 143.5 |
| North East | England | Listeriosis [3] | 8 | 0.29 |
| North East | England | Non-typhoidal Salmonella [3] | 471 | 17.1 |
| North West | England | Campylobacter [3] | 10,110 | 130.7 |
| North West | England | Listeriosis [3] | 23 | 0.30 |
| North West | England | Non-typhoidal Salmonella [3] | 1,273 | 16.5 |
| South East | England | Campylobacter [3] | 12,668 | 131.4 |
| South East | England | Listeriosis [3] | 27 | 0.28 |
| South East | England | Non-typhoidal Salmonella [3] | 1,685 | 17.5 |
| South West | England | Campylobacter [3] | 7,925 | 134.6 |
| South West | England | Listeriosis [3] | 18 | 0.31 |
| South West | England | Non-typhoidal Salmonella [3] | 896 | 15.2 |
| West Midlands | England | Campylobacter [3] | 7,400 | 119.6 |
| West Midlands | England | Listeriosis [3] | 17 | 0.27 |
| West Midlands | England | Non-typhoidal Salmonella [3] | 921 | 14.9 |
| Yorkshire and the Humber | England | Campylobacter [3] | 5,682 | 100.2 |
| Yorkshire and the Humber | England | Listeriosis [3] | 20 | 0.35 |
| Yorkshire and the Humber | England | Non-typhoidal Salmonella [3] | 902 | 15.9 |
| Ayrshire & Arran | Scotland | Campylobacter [4] | 331 | 90.1 |
| Ayrshire & Arran | Scotland | Non-typhoidal Salmonella [4] | 63 | 17.2 |
| Borders | Scotland | Campylobacter [4] | 205 | 175.5 |
| Borders | Scotland | Non-typhoidal Salmonella [4] | 16 | 13.7 |
| Dumfries & Galloway | Scotland | Campylobacter [4] | 297 | 204.1 |
| Dumfries & Galloway | Scotland | Non-typhoidal Salmonella [4] | 31 | 21.3 |
| Fife | Scotland | Campylobacter [4] | 535 | 143.1 |
| Fife | Scotland | Non-typhoidal Salmonella [4] | 55 | 14.7 |
| Forth Valley | Scotland | Campylobacter [4] | 176 | 57.5 |
| Forth Valley | Scotland | Non-typhoidal Salmonella [4] | 47 | 15.4 |
| Grampian | Scotland | Campylobacter [4] | 621 | 105.3 |
| Grampian | Scotland | Non-typhoidal Salmonella [4] | 79 | 13.4 |
| Greater Glasgow & Clyde | Scotland | Campylobacter [4] | 1,248 | 102.3 |
| Greater Glasgow & Clyde | Scotland | Non-typhoidal Salmonella [4] | 200 | 16.4 |
| Highland | Scotland | Campylobacter [4] | 384 | 118.3 |
| Highland | Scotland | Non-typhoidal Salmonella [4] | 45 | 13.9 |
| Lanarkshire | Scotland | Campylobacter [4] | 933 | 137.6 |
| Lanarkshire | Scotland | Non-typhoidal Salmonella [4] | 126 | 18.6 |
| Lothian | Scotland | Campylobacter [4] | 979 | 104.7 |
| Lothian | Scotland | Non-typhoidal Salmonella [4] | 142 | 15.2 |
| Orkney | Scotland | Campylobacter [4] | 35 | 159.7 |
| Orkney | Scotland | Non-typhoidal Salmonella [4] | <5 | 13.7 |
| Shetland | Scotland | Campylobacter [4] | 44 | 193.7 |
| Shetland | Scotland | Non-typhoidal Salmonella [4] | <5 | 13.2 |
| Tayside | Scotland | Campylobacter [4] | 514 | 123.0 |
| Tayside | Scotland | Non-typhoidal Salmonella [4] | 63 | 15.1 |
| Western Isles | Scotland | Campylobacter [4] | 42 | 163.0 |
| Western Isles | Scotland | Non-typhoidal Salmonella [4] | <5 | 7.8 |
England’s regional counts use the annual reports, which total 69,394 Campylobacter and 10,406 Salmonella reports; subsequent national revisions are not assigned to regions. Scottish rates use Appendix 2: Greater Glasgow & Clyde and Grampian Salmonella rates are 16.4 and 13.4, which differ from the main results table. The source discrepancy is recorded in the download. “<5” means suppressed, not zero.
E. coli and STEC: case definitions matter
England recorded 2,457 culture-confirmed STEC cases in 2025: 568 O157 and 1,889 non-O157. The culture-confirmed total was 3.4% below 2024. A further 961 non-O157 reports were PCR-positive without culture confirmation. Including those gives 2,850 non-O157 reports, a different reporting group. [3]
England · 2025 · Different diagnostic groups [3]
PCR-only reports are shown separately from the 2,457 culture-confirmed cases. More widespread PCR testing can change detection, especially for non-O157 infections.

| Clinical outcome | O157 | Non-O157 |
|---|---|---|
| Symptomatic cases with clinical information | 513 | 878 |
| Hospitalised among that group | 134 (26.1%) | 243 (27.7%) |
| HUS recorded | 7 of 568 reports | 32 of 2,850 reports |
| Reported deaths | 0 | 3 |
HUS, haemolytic uraemic syndrome, is a serious complication affecting the kidneys and blood. The hospitalisation percentages use symptomatic cases with clinical information. Outcome information is incomplete, especially for non-O157 reports, so these percentages should not be applied to all exposed people or all infections.
Listeriosis: fewer cases, serious consequences
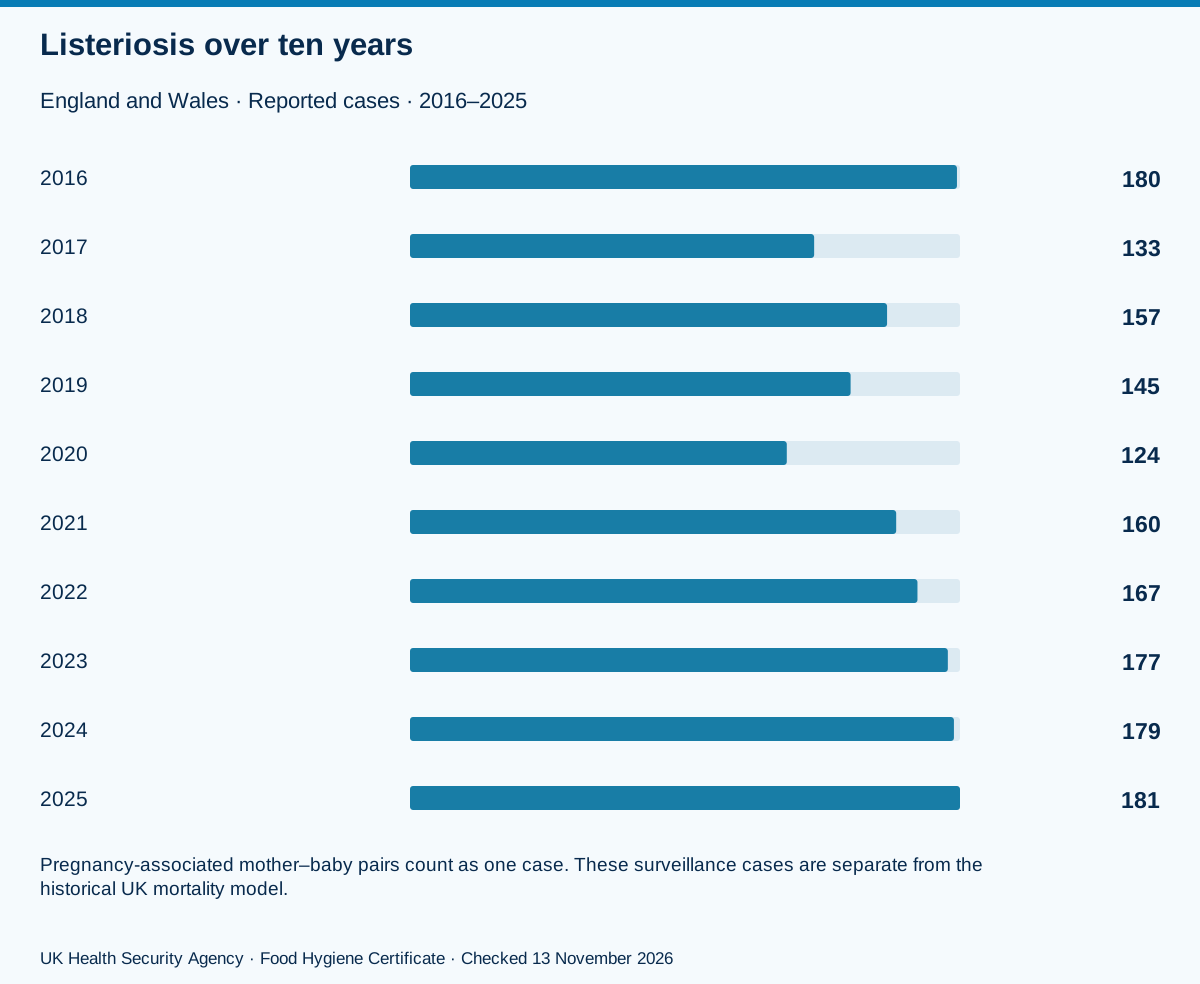
There were 181 listeriosis cases in England and Wales in 2025. Forty were pregnancy-associated and 141 were non-pregnancy-associated. Surveillance counts a mother and baby as one case. [3]
England and Wales · Reported cases · 2016–2025 [3]
Pregnancy-associated mother–baby pairs count as one case. These surveillance cases are separate from the historical UK mortality model.
| 2025 outcome | Published count | Relevant group |
|---|---|---|
| Live birth | 24 | 40 pregnancy-associated cases |
| Stillbirth | 5 | 40 pregnancy-associated cases |
| Miscarriage | 6 | 40 pregnancy-associated cases |
| Pregnancy outcome unknown | 5 | 40 pregnancy-associated cases |
| Deaths among non-pregnancy cases | 28 | 141 non-pregnancy-associated cases |
| Listeriosis recorded as a cause of death | 17 | Within the reported deaths; cause records may be incomplete |
Stillbirth or miscarriage was recorded in 11 of the 35 pregnancies with a known outcome, or 31.4%. This describes a small group of diagnosed pregnancy-associated listeriosis cases; it is not the risk for everyone who eats a particular food. Likewise, deaths among patients are not identical to deaths attributed to the infection.
Norovirus: foodborne estimates and current activity
The historical UK model estimates 383,182 foodborne norovirus illnesses annually. The source table does not publish an uncertainty interval for that particular estimate. This estimates illness transmitted through food, rather than all norovirus infections. [1] See our norovirus statistics for the wider surveillance context.
The newest England surveillance report recorded 2,111 laboratory reports during weeks 27–45 of the 2026/27 season, through 8 November 2026. That was 16.8% above the five-season comparison average of about 1,807. This is current activity from all transmission routes, including person-to-person spread; it must not be described as 2,111 food-poisoning cases. [5]
England · 2026/27 season · Weeks 27–45, ending 8 November 2026 [5]
All transmission routes, not foodborne-only. Recent weeks can rise after late reports. Future weeks are omitted, not counted as zero.
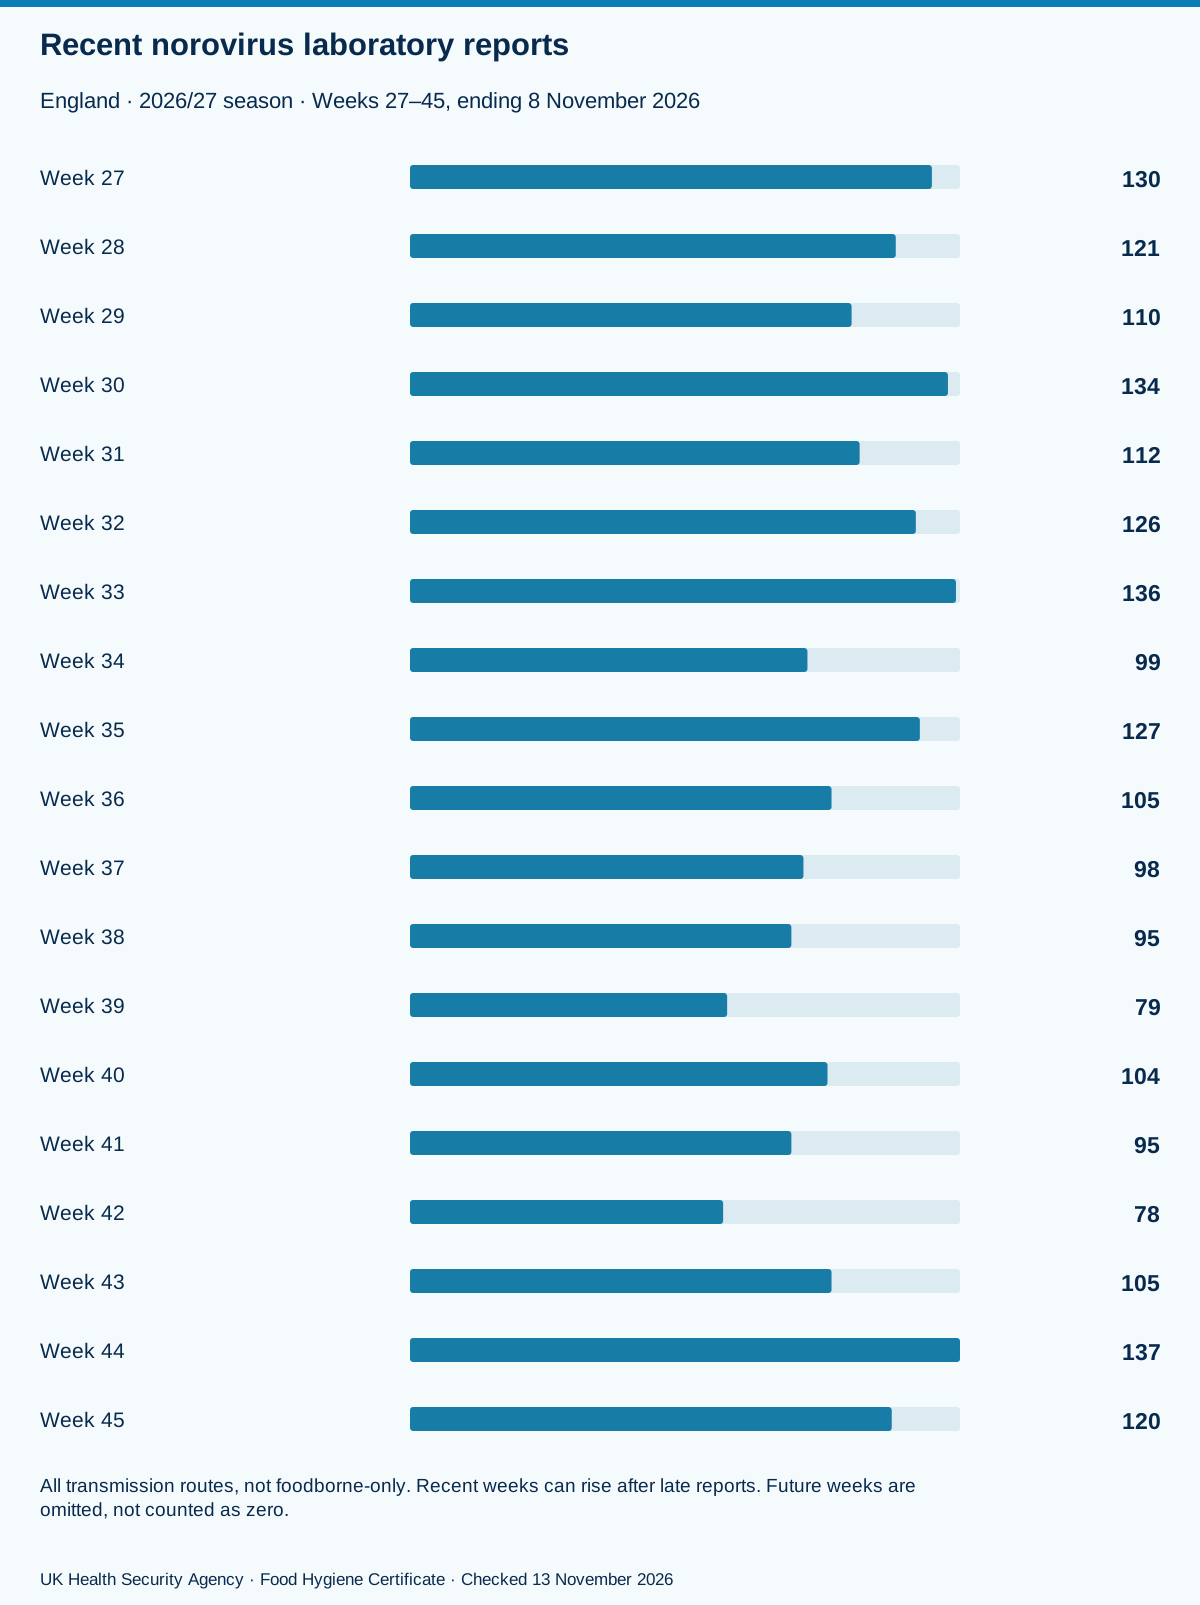
The latest surveillance season and the historical foodborne model have different populations, dates and methods. Their counts should not be added, and dividing one by the other would not give a reliable current foodborne share.
Food poisoning outbreaks: foods, settings and outcomes
UKHSA reported seven foodborne Campylobacter outbreaks and thirteen non-typhoidal Salmonella outbreaks in England in 2025. The Campylobacter outbreaks affected 30 people, with 20 laboratory-confirmed cases and eight reported hospital admissions. The Salmonella outbreaks affected 269 people, with 258 laboratory-confirmed cases and 33 reported admissions. Outcome information was incomplete. [3]
The largest listed outbreak involved imported eggs: 122 affected and laboratory-confirmed cases, with twelve reported hospitalisations. A watermelon-associated Salmonella outbreak affected 23 people. The evidence linking a food varies between investigations, so that strength is retained in the table.
All published records are shown below.
| Infection / agent | Setting | Food implicated or suspected | Affected | Lab confirmed | Reported admissions | Evidence |
|---|---|---|---|---|---|---|
| Non-typhoidal Salmonella S. Enteritidis | National | Imported eggs | 122 | 122 | 12 | Strong |
| Non-typhoidal Salmonella S. Typhimurium | National | Not identified | 31 | 31 | 7 | Not applicable |
| Non-typhoidal Salmonella S. Enteritidis | Small Retailer | Shelled eggs and imported poultry | 25 | 25 | 0 | Weak |
| Non-typhoidal Salmonella S. Saintpaul | National | Watermelon | 23 | 23 | 2 | Strong |
| Non-typhoidal Salmonella S. Typhimurium | Restaurant | Dairy ice cream | 18 | 16 | 3 | Weak |
| Non-typhoidal Salmonella S. Typhimurium | National | Not identified | 17 | 17 | 5 | Not applicable |
| Non-typhoidal Salmonella S. Newport | Takeaway restaurant | Raw onions | 9 | 4 | 0 | Weak |
| Campylobacter Campylobacter species | Care home | Unknown | 6 | 1 | Not reported | Not specified in table |
| Non-typhoidal Salmonella S. Enteritidis | Restaurant | Not identified | 6 | 6 | 0 | Not applicable |
| Campylobacter Campylobacter species | Pub | Lamb liver | 5 | 2 | 2 | Not specified in table |
| Campylobacter C. jejuni | Hospital | Unknown | 5 | 5 | 5 | Not specified in table |
| Non-typhoidal Salmonella S. Montevideo | Nursery | Not identified | 5 | 5 | 1 | Not applicable |
| Non-typhoidal Salmonella S. species | Prison | Not identified | 5 | 3 | 1 | Not applicable |
| Campylobacter Campylobacter species | Restaurant | Chicken | 4 | 2 | 0 | Not specified in table |
| Campylobacter C. jejuni | Other | Unknown | 4 | 4 | 1 | Not specified in table |
| Non-typhoidal Salmonella S. Typhimurium | Restaurant | Poultry | 4 | 2 | 0 | Weak |
| Campylobacter C. jejuni | Self-catered event | Unknown | 3 | 3 | 0 | Not specified in table |
| Campylobacter C. jejuni | National | Chicken | 3 | 3 | Not reported | Not specified in table |
| Non-typhoidal Salmonella S. Coeln | Restaurant | Poultry | 2 | 2 | 0 | Weak |
| Non-typhoidal Salmonella S. Kentucky | Hospital | Not identified | 2 | 2 | 2 | Not applicable |
Download all twenty outbreak records (CSV)
This table is not every foodborne outbreak or every illness in England. Some foods were unknown or not identified; a setting such as a restaurant or hospital does not prove where every exposure occurred. The four listeriosis outbreaks investigated in 2025 included cases from earlier years, so their multi-year totals are not added to these annual counts. [3]
Which foods and food-handling routes appear in the evidence?
The outbreak table identifies foods such as eggs, poultry, lamb liver, watermelon, ice cream and raw onions. It describes detected outbreaks rather than the risk per serving. A food involved in a large outbreak is not automatically the riskiest food in everyday use. [3]
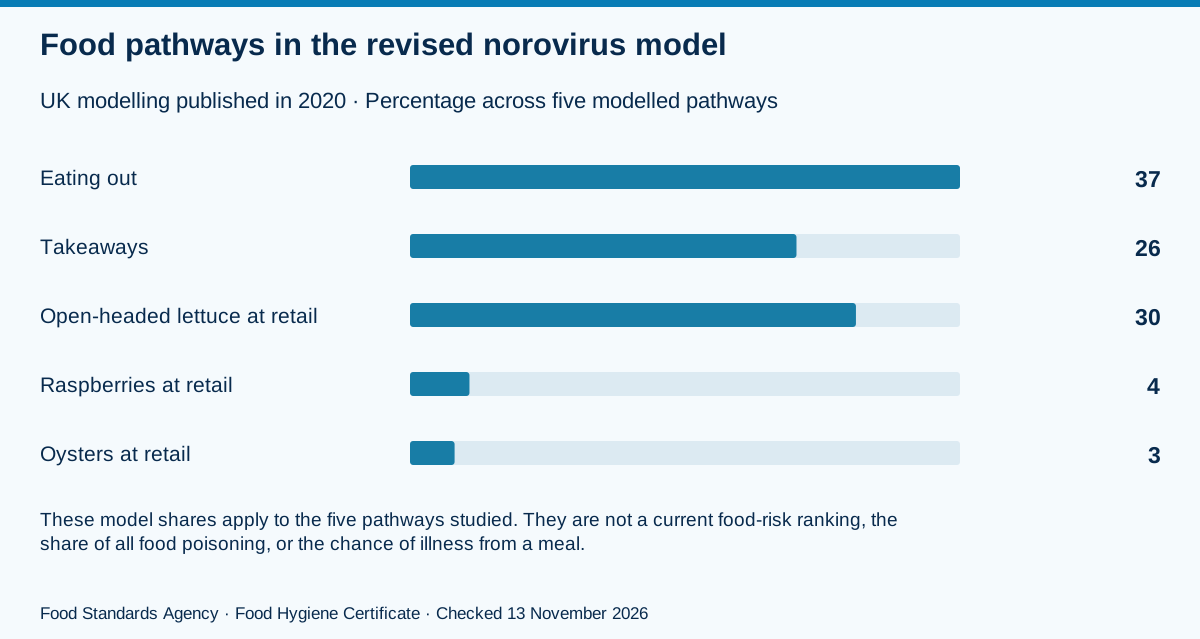
The FSA’s revised 2020 norovirus assessment modelled five food pathways. Their estimated shares were 37% eating out, 26% takeaways, 30% open-headed lettuce at retail, 4% raspberries at retail and 3% oysters at retail. These are shares within that historical modelling exercise, not measured 2026 shares of all UK food poisoning. [8]
UK modelling published in 2020 · Percentage across five modelled pathways [8]
These model shares apply to the five pathways studied. They are not a current food-risk ranking, the share of all food poisoning, or the chance of illness from a meal.
A 2025 FSA review examined food attribution for enteropathogenic E. coli (EPEC), hepatitis A, sapovirus and Toxoplasma gondii. It compared research using different methods and countries. That makes it useful for understanding evidence gaps, but it does not supply one new, directly measured UK percentage for every food. [8]
How many deaths and hospital admissions are linked to food poisoning?
The FSA’s 2018 burden model estimates 16,439 annual foodborne hospital admissions, commonly rounded to 16,400. Its 95% credible interval is 11,410–26,119. A narrower total excluding listeriosis is 16,301; that distinction explains why some summaries use approximately 16,300. [1]
A separate mortality study estimated 180 annual UK foodborne deaths from eleven pathogens, with a 95% credible interval of 113–359. It was published in 2020 using historical inputs. It is not a count of deaths registered in 2025 or 2026, and it does not estimate every unidentified foodborne cause. [6]
| Pathogen | Estimated annual foodborne deaths | 95% credible interval |
|---|---|---|
| Norovirus | 56 | 32–92 |
| Salmonella | 33 | 7–159 |
| Listeria monocytogenes | 26 | 24–28 |
| Clostridium perfringens | 25 | 1–163 |
| Campylobacter | 21 | 8–47 |
The uncertainty intervals overlap substantially. The central estimates should not be turned into a precise ranking of the deadliest pathogens. The mortality study uses pathogen-specific preferred models, which are separate from the illness and hospital-admission model.
How much does food poisoning cost the UK?
The FSA’s latest verified valuation is £11.8 billion a year at 2025 prices. Its September 2026 science update, revised on 19 October, describes this as the annual societal cost of microbiological foodborne disease. The estimate includes financial costs and the value of harm to people. [7]
This is not an NHS bill or the amount businesses spend on treatment. The original model separates healthcare, lost earnings, individual expenses, disruption to businesses and human harm. The chart below shows the published components of the older 2018-price model to explain that composition; it is not a breakdown of the £11.8 billion valuation.
UK · Component medians in £ million · 2018 prices [7]
Historical component medians, not current spending. Components need not sum exactly to the overall model median. Human costs value harm and are not cash expenditure.
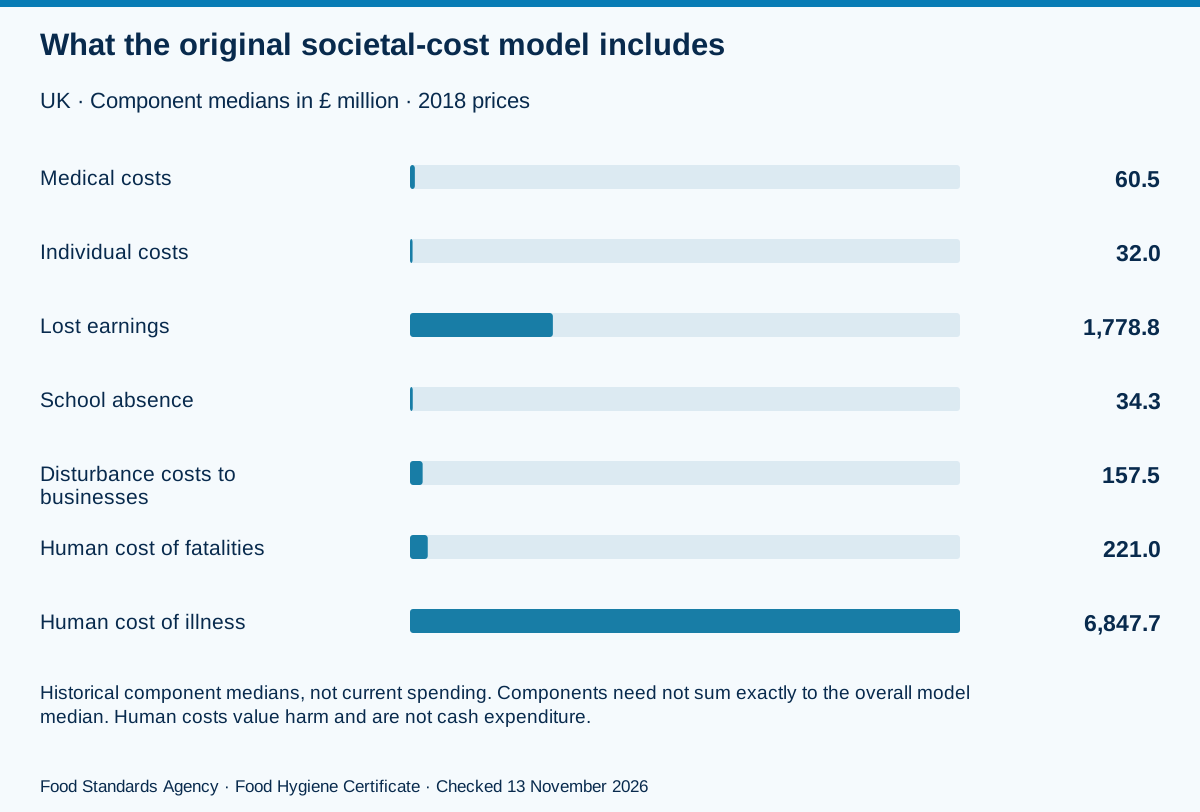
Updating prices changes a valuation even without a measured change in illness. Comparing the original model’s price-year total with £11.8 billion therefore cannot establish an increase in food poisoning. The downloadable record keeps the reference and price years separate.
Food-safety incidents are a separate measure
The FSA was notified of 2,073 food and feed safety incidents in England, Wales and Northern Ireland during 2025/26, 14% more than the preceding year. Incidents can concern contamination or other hazards without a confirmed human illness. [9]
| Operational measure | 2025/26 figure | Meaning |
|---|---|---|
| All food and feed safety incidents | 2,073 | Incidents notified to the FSA, not people affected |
| Salmonella incidents | 206 | 50% of pathogenic micro-organism incidents, as rounded by FSA |
| Listeria incidents | 92 | 22% of pathogenic micro-organism incidents |
| E. coli / STEC incidents | 57 | 13% of pathogenic micro-organism incidents |
| Reported foodborne outbreaks | 25 | Investigations with evidence of a common source |
| Clusters of interest | 29 | A common source could not be established |
The 25 outbreaks and 29 clusters total 54 investigations, down from 66 in 2024/25. One related to animal health with potential food or feed implications; the remainder concerned human health. These operational figures overlap other surveillance and use a financial year, so they must not be added to UKHSA’s calendar-year outbreak counts.
Who is most affected, and who is most vulnerable?
Reported infection and the risk of serious complications are different measures. England’s 2025 Campylobacter report says 55% of reports with demographic data were male, and 43.0% of reports concerned people aged 50–79. For Salmonella, 20.3% of reports concerned children aged 0–9. These shares describe diagnosed reports, rather than everyone infected. [3]
Scotland’s 2025 Campylobacter reporting rates were 128.9 per 100,000 males and 101.2 per 100,000 females. Its highest older-age rate was 157.9 among people aged 65 and over. Non-typhoidal Salmonella reporting was highest among children aged 0–4, at 37.4 per 100,000. These are crude reporting rates, not adjusted comparisons of food exposure. [4]
Young children, older people, pregnant women and people with weakened immune systems can face greater consequences from particular foodborne infections. The listeriosis pregnancy figures and STEC outcomes above show why food-specific advice matters, even when the number of detected cases is comparatively small. [10]
What the evidence means for food safety
Use the FSA’s four principles—cleaning, cooking, chilling and preventing cross-contamination—as part of everyday controls. Handwashing, separating raw and ready-to-eat food, following use-by dates and using suitable time-and-temperature checks address routes that appear repeatedly in outbreak investigations. [10]
One recognised cooking combination is 70°C for two minutes at the centre of the food; 75°C for 30 seconds is an alternative. Set refrigerators to 5°C or below and follow each product’s storage instructions. These are practical guidance values, rather than statistics about infection frequency. [10]
A food-hygiene rating describes conditions at inspection; it cannot guarantee a future meal is safe. For more detail, see our food hygiene rating statistics and food poisoning outbreak guide.
Food Hygiene Certificate compiled this guide from the original research and surveillance listed below. Our Level 2 food hygiene course covers practical food-handling responsibilities, while Level 3 training supports supervisors and managers.
Download the charts and evidence
Use the figures with their original period, geography and definition. Each chart download includes a matching CSV; the complete evidence record includes source locations, uncertainty intervals, revisions and calculation notes.
Food Hygiene Certificate (2026). Food Poisoning Statistics UK: 2026 Facts, Data & Key Insights. Evidence checked 13 November 2026. https://www.foodhygienecertificate.co.uk/blog/food-poisoning-statistics-uk
Sources and methodology
Figures are compiled from the original publishers below. Each numbered reference identifies the relevant source group; exact tables and rows are included in the downloads.
- FSA: the UK foodborne disease model
Original 2018-reference model, published in 2020; Table 3 supplies pathogen estimates and uncertainty. Preserved by the UK Government Web Archive.
- UKHSA: latest Campylobacter and Salmonella quarterly surveillance
Published 24 September 2026; extracted 21 August. England, Q1 2024–Q2 2026. Revised national totals and partial-year comparisons.
- UKHSA: annual bacterial surveillance
2025 annual reports supply earlier decade observations, regional comparisons, age findings and the 20 outbreak records. Regional totals retain this edition and differ slightly from later national revisions.
- Public Health Scotland: 2025 gastrointestinal surveillance
Published 10 November 2026. Scotland annual counts and NHS board comparisons. These are laboratory reports, not a count of foodborne-only illness.
Campylobacter by board · Salmonella by board · Board reporting rates
- UKHSA: current norovirus surveillance
Week 46 report, published 12 November 2026, covering weeks 27–45 through 8 November. England laboratory reports from all transmission routes.
- FSA-authored research: deaths from 11 foodborne pathogens
Published in 2020. Pathogen-specific preferred models, Table 4. Modelled annual deaths and 95% credible intervals, not registered deaths in 2025 or 2026.
- FSA: societal costs and the latest research update
September 2026 Board paper, updated 19 October: £11.8 billion at 2025 prices, Annex 3 section 3. Historical cost components below come from the separate original 2018-price model.
- FSA: food attribution research
2025 review of EPEC, hepatitis A, sapovirus and Toxoplasma gondii considers studies with different countries, methods and periods; it is not a new measured UK food-risk league table.
- FSA: Incidents and Resilience Annual Report 2025/26
Published 25 June 2026. Sections 2.2, 2.9–2.10: incidents and outbreak investigations in England, Wales and Northern Ireland; not counts of ill people.
- FSA and NHS: food safety guidance
Practical guidance accompanies the evidence; food handlers should follow their business food-safety procedures.
Definitions, revisions and calculations
Percentage change is (new value ÷ earlier value − 1) × 100, rounded to one decimal place. First-half totals add Q1 and Q2 from the same release. The England decade charts use annual reports for 2016–2023 and September 2026 national revisions for 2024–2025. The regional table retains the annual editions because equivalent revised regional data are not supplied.
Scottish regional rates come from Appendix 2. Two Salmonella rates conflict with Table 10.1; both published values and our selected source are preserved in the evidence record. Suppressed counts remain <5; unknown clinical outcomes remain unknown.
Model medians and credible intervals are distinct from observed reports and confidence intervals. Separate medians do not necessarily sum exactly. Laboratory reports include non-foodborne transmission; country definitions and STEC testing groups differ. No combined UK case total or area risk ranking is constructed.
Cost figures retain their price year. Modelled illness, GP presentations, admissions and mortality are not treated as one patient cohort. Historical food-attribution findings are not presented as current exposure probabilities.